
Health and aged care
Nurse call, monitoring and clinical systems
Care technology is usually specified inwards from the product: a system is chosen, then people are asked to work around it. Ericom starts at the person being cared for, works out to the staff around them and the organisation accountable for both, and puts the technology in last.
Whose problem is it
A care facility rarely buys one thing. It buys a nurse call system, then a network, then cameras, then whatever the last capital works project left behind. Each came from a different supplier, and each was commissioned and walked away from.
All of them work. What has no owner is the path a call takes between them: from the pendant to the annunciator, from the annunciator to the handset, from the handset to a person on shift who has to respond. The duty of care is one obligation. The path it depends on runs across four contracts.
-
The call did not reach the handset
Was that the nurse call system, the paging infrastructure or the handset itself? Three suppliers, three answers, and none of them obviously wrong.
-
The sensor stopped reporting
The sensor, the network it rides on, or the server that should be recording it. Each will check their own layer, find it healthy, and say so.
-
No records for three weeks
Somebody has to notice first. Reporting failures are silent by nature, and silence belongs to whoever is not looking for it.
In an office, working out whose problem it is wastes a morning. In a building where somebody has fallen, it costs more than that, and the review afterwards has to establish from four suppliers' logs what happened and when. These are IP systems now, running on structured cabling, so one team can install them, monitor them and answer for all of them. Most care buildings have never been set up that way.
The same equipment, asked different things
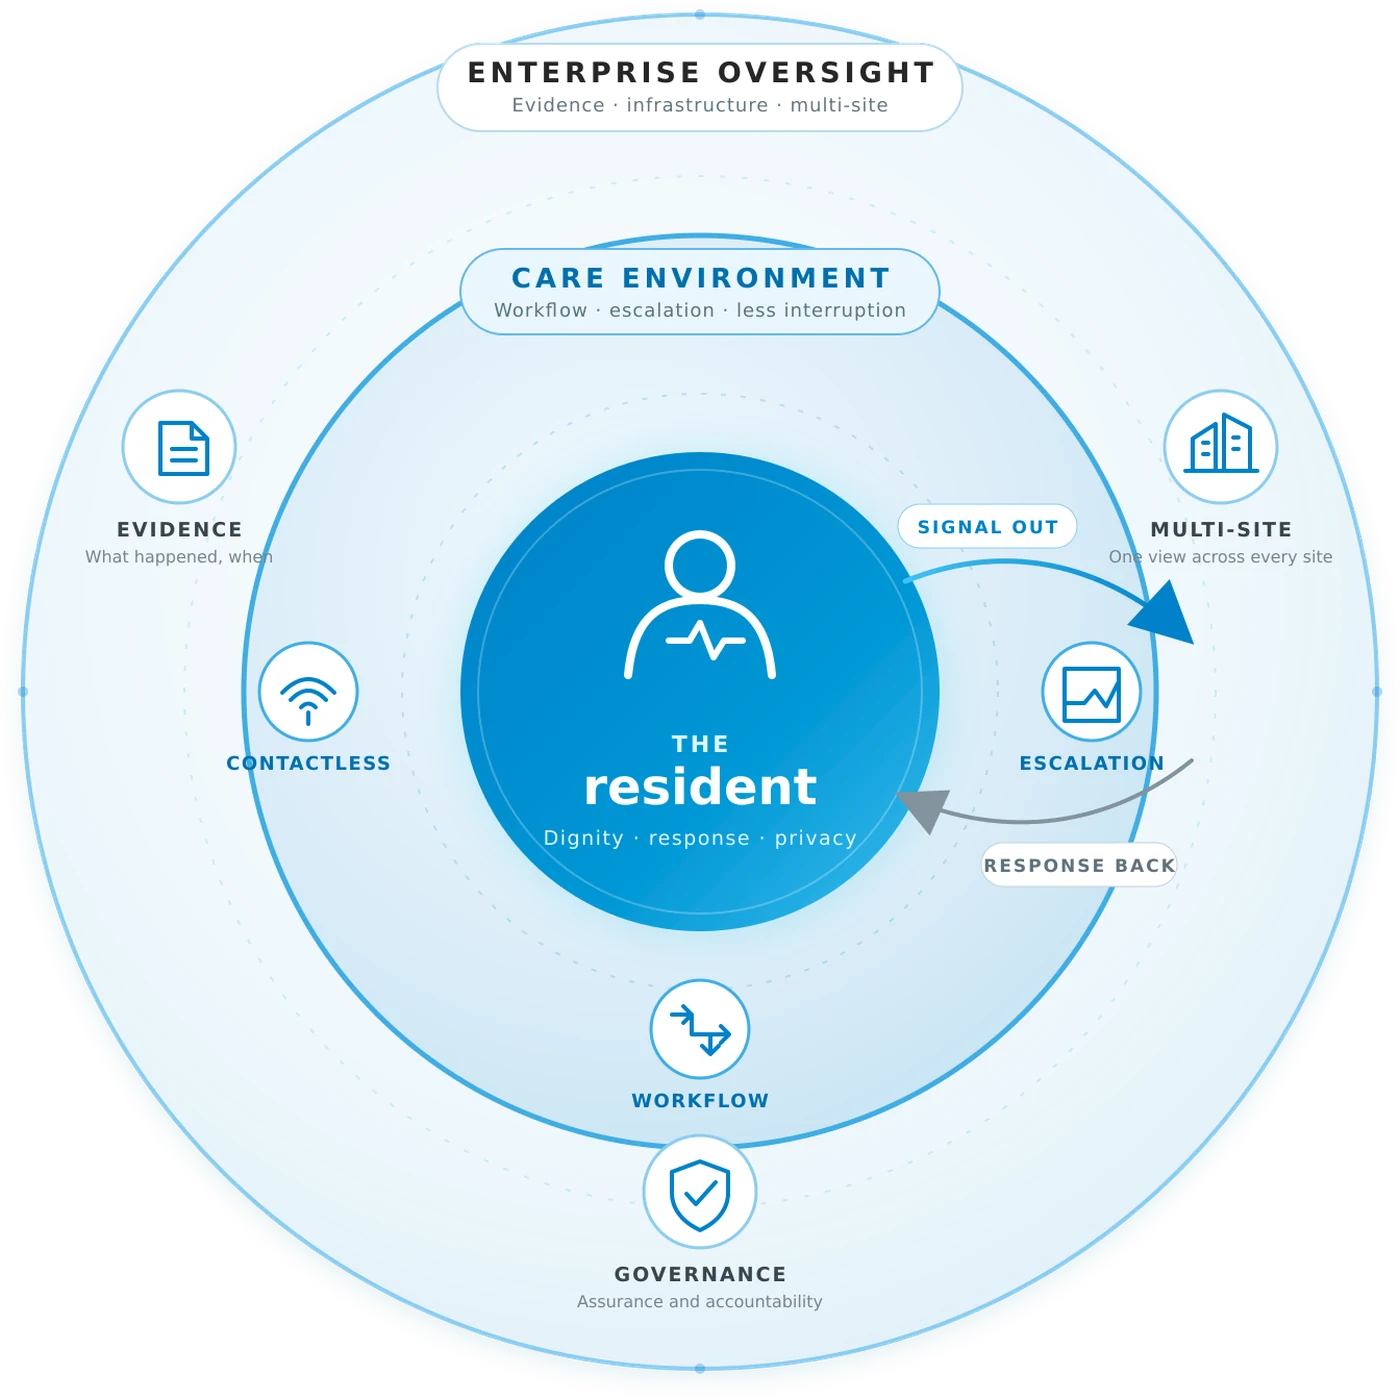
The same equipment is asked for different things depending on who is looking at it. Designing for one layer and hoping the others cope is how care technology ends up resented.
-
The resident
Dignity first. A call answered, a deterioration noticed early, and as little equipment in the room as the job allows. That is why the vital signs sensing is contactless and produces no image at all.
-
The care environment
Staff who are already stretched need fewer interruptions, not more data. The measure of a good deployment is how much it raises, not how much it can detect.
-
Enterprise oversight
Boards and quality teams need evidence: what happened, when, who attended and how long it took, across every site at once. That evidence is produced by the reporting and the infrastructure underneath, so it is designed in from the start rather than assembled when an auditor asks.
What we bring to a care setting
Each of these is a solution in its own right and is documented as one. What changes here is the question it is asked.
- Nurse Call The call system itself, replaced room by room while the building stays open and full, then monitored like the rest of your infrastructure. The resident
- Vital Signs Monitoring Contactless radar in the room. No camera, no wearable, and a signal that a resident's condition is changing before it presents. The resident
- Intelligent Video Analytics The cameras already in the corridors, asked a narrow question: a fall where no pendant was pressed, a door opened at night by someone who should not be leaving. Each rule is tuned against the cost of the alert being wrong, because in a care building a false one is paid for by the next one. The care environment
- Distributed Antenna Systems The handset is the last link in the path from pendant to person, and the lift, the basement and the plant room are where it drops. Coverage engineered for the building, so the page and the duress call arrive where staff actually are. The care environment
- IT Support The workstations at the nurses' station, the identities of rostered and agency staff who sign into them, the clinical applications behind those sign-ins, and the servers and network devices the building runs on. A ward runs all night and the service desk does not, so monitoring and severity-one escalation are what stand between the two. Enterprise oversight
- Essential Eight Resident records are health data, and a breach of them is a clinical governance matter as much as an IT one. The Essential Eight gives a clinical governance committee a scale to ask about: which of the eight strategies the organisation is aligned to, at what maturity level, and what would show it if a regulator or an insurer asked. Enterprise oversight
The alert has to be believed
Every alert that turns out to be nothing spends a little of the credibility of the next one. In a care setting that currency is finite and it is not recoverable. A system nobody trusts by month six is worse than no system, because the building has stopped listening while believing it is covered.

“The speed and quality of the work has been very impressive, and while we scoped the project out early, the dynamic nature of the COVID period has allowed us to shift priorities, and I appreciate your recommendations and agile approach.”
IT Manager, St John Ambulance Australia (VIC)
Common questions
Do you work in hospitals as well as aged care?
Both. The scoping differs considerably. Bed numbers, care model, annunciator placement, escalation and after-hours coverage all change between a residential aged care facility and a hospital ward, so the two are quoted differently even where the platform is the same.
Do we have to take all of it?
No. Most start with the one that is failing. Each of these is sold and delivered on its own. They compound because they share the cabling, the network and the team supporting them, and that shared layer is where a fault hides when four suppliers each find their own part healthy.
Are these products built specifically for healthcare?
Nurse call is. The sensing platforms are not. Contactless vital signs and video analytics are also deployed in custodial and commercial environments. We think that counts in their favour, and we would rather you heard it here than found out later.
Who makes the clinical decisions?
You do, always. Which alerts are raised, at what threshold, which handset each one lands on and what happens if it is not answered are yours to set, and we build and support the system to match. Where the result looks likely to be alerts staff learn to ignore, we say so before it is commissioned, while the building is still listening.
Where does the data stay?
Onshore. Ericom supplies, integrates and runs these systems in Australia, which matters more here than in most sectors because the data concerns residents' bodies and their movements.
Where the path breaks
Bring the calls that are not reaching a handset, the alerts staff have stopped answering, and the incident review that could not say what happened. A site survey traces each of those to the layer that owns it: the device, the network, the cabling or the contract. What comes back is what is failing, where it sits, and who has to fix it. Victorian services also have our Melbourne office to call on.
Request a site survey